

Interventional Pain Management for Back Pain in Portland: Targeted, Diagnosis-Guided Care
- Home
- Interventional Pain Management for Back Pain in Portland: Targeted, Diagnosis-Guided Care
Living with chronic back pain in Portland often means quietly editing your life around it, skipping a walk along the waterfront, dreading a long day at a downtown desk, or leaving a Moda Center game early because sitting has become the hardest part of the night. Advanced Pain Management Center takes a diagnosis-guided approach to determining what may be contributing to the pain and which treatment options may be appropriate.
At 10305 SW Park Way, Suite 300, in Portland’s West Haven area, the team evaluates each patient’s symptoms, examination findings, imaging, previous treatment, and individual goals before recommending care. Under the care of interventional pain physician Vladimir Fiks, MD, the practice offers image-guided and minimally invasive options that may include spinal injections, radiofrequency ablation, decompression and stabilization procedures, spinal cord or peripheral nerve stimulation, and other interventional treatments selected according to the patient’s condition.
Schedule Your Portland Back Pain Evaluation | Call (503) 295-0730
Finding the SW Park Way Office From Downtown Portland and the East Side
The office is located at 10305 SW Park Way, Suite 300, in the West Haven area of southwest Portland near Providence St. Vincent Medical Center. Patients visit from Downtown Portland, the Rose Quarter, South Waterfront, and other parts of the metro area using routes that may include US-26 and I-405. Travel time varies according to the patient’s starting point, traffic, and appointment time. Patients can contact the office for current parking, entrance, and accessibility guidance.
The west-side location also serves patients from Beaverton, Tigard, Hillsboro, Lake Oswego, the greater Portland area, and Southwest Washington. Depending on the starting point, patients may use US-26, Highway 217, or other regional routes. Weekday office hours provide several options for planning an evaluation or follow-up appointment.
The Portland Practice Built Around Evaluating What May Be Causing Your Back Pain
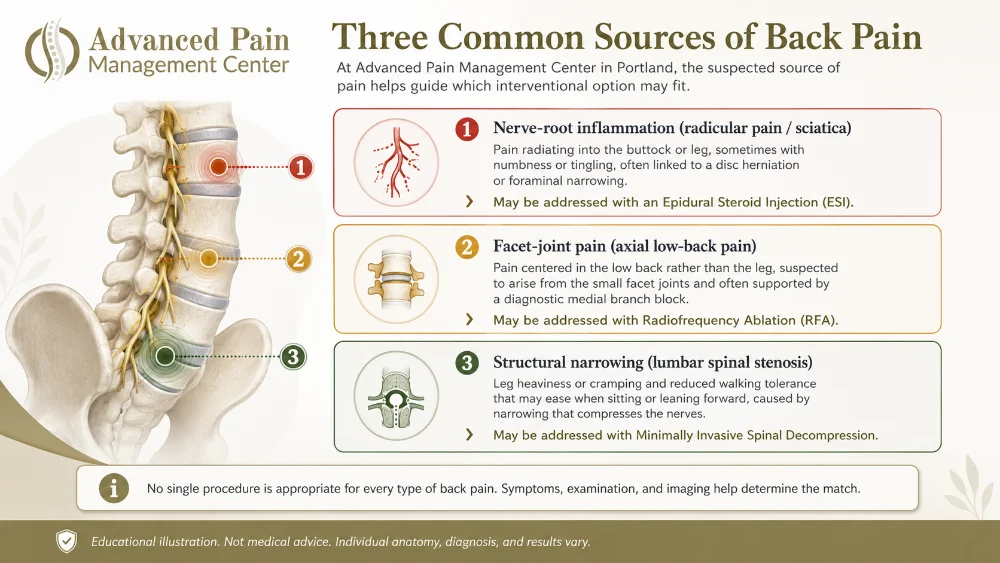
Many people living with chronic back pain have already tried treatments that eased their symptoms temporarily without clarifying why the pain persisted. Advanced Pain Management Center was built around a different approach. Since opening in Portland in 2000, the practice has focused on interventional pain medicine, combining clinical evaluation with image-guided procedures selected according to the suspected structure or nerve contributing to the pain. Because back pain is a symptom rather than one diagnosis, the plan considers whether an irritated nerve root, an arthritic facet joint, a narrowed spinal canal, or another condition may be involved.
The patients who come to the SW Park Way office reflect the range of ways back pain shows up. Some are desk-bound downtown professionals whose lower back tightens after long hours at a screen. Some are active Portland adults whose pain sits deep in the low back and flares with twisting or bending. Others are older patients whose legs grow heavy and tired after a block or two of walking. Each pattern may suggest a different contributing condition. The evaluation considers the symptoms, examination findings, imaging, and previous treatment before any procedure is recommended.
Why Portland Patients Bring Their Back Pain to Advanced Pain Management Center
Patients who choose Advanced Pain Management Center often value its diagnosis-guided evaluation, range of interventional options, and compassionate support. In their reviews, patients describe a progressive team that continues exploring appropriate options for persistent pain.
- A diagnosis-first approach: the team evaluates the likely source and contributing factors behind the back pain before recommending treatment because the appropriate option depends on the diagnosis and clinical findings
- Physician-performed spine procedures: Vladimir Fiks, MD, performs the practice’s minimally invasive spinal decompression procedures himself, with the physician assistants and nursing staff supporting candidate selection and recovery
- Regenexx-trained interventional physician: Dr. Fiks is a Regenexx physician with experience in image-guided interventional orthopedic care and minimally invasive spine procedures
- Image-guided procedures: fluoroscopic or, when appropriate, ultrasound guidance is used to help guide treatment toward the intended anatomical target
- Diagnostic blocks before ablation: a medial branch block is generally used before radiofrequency ablation to assess whether facet-mediated pain is likely and whether ablation may be appropriate
- A broad interventional toolkit: treatment options may include epidural injections, radiofrequency ablation, minimally invasive decompression and stabilization, SI joint and lumbar fusion, spinal cord and peripheral nerve stimulation, spinal infusion, and related procedures selected according to the patient’s diagnosis and treatment goals
- Minimally invasive, outpatient care: many of the practice’s interventional procedures are performed on an outpatient basis, with the specific anesthesia, sedation, recovery, and discharge plan depending on the treatment
- An option before major spine surgery: for selected patients, interventional care may provide an alternative treatment path before a larger operation is considered, though candidacy depends on the individual diagnosis and clinical circumstances
- Coordinated whole-person care: the team refers patients to trusted outside health care partners for physical therapy and behavioral support when those services would help
- Multilingual physician care: Dr. Fiks speaks English, Spanish, and Russian
- Serving Portland since 2000: the practice has focused on pain diagnosis and treatment in the West Haven medical corridor for more than two decades
These reviews describe individual patient experiences. Treatment recommendations, recovery, and results vary.
“Excellent pain clinic with all of the latest technology and very compassionate staff who are very progressive, and constantly helping me find both conventional and innovative new solutions. They have been the best partner ever in helping me to improve my chronic, severe back pain issues. I’m a very happy patient and recommend them to anyone who struggles with chronic pain. I have sent several friends their way since I know first hand the amazing help that they’ll get. I’m a scuba diver and with their help just did a 9 day dive vacation and was able to do 3 dives a day again every day we were there, 18 dives total! Thank you APM for helping me get my life back!”
What Interventional Back Pain Care Aims to Achieve for Portland Patients
Interventional care is organized around the diagnosis, functional limitations, and individual treatment goals rather than a promise to cure. Different procedures address different contributors to back pain, so the appropriate approach depends on the symptoms, examination findings, imaging, previous treatment, and overall clinical picture.
Relief From Radiating Leg Pain and Sciatica
When back pain travels into the buttock or leg because a spinal nerve root is irritated or inflamed, an epidural steroid injection may help reduce inflammation and ease radiating nerve-related symptoms, often described as sciatica. It does not repair a disc or reverse structural narrowing, and relief is generally temporary. Whether an injection is appropriate depends on how well the patient’s symptoms, examination, and imaging findings align.
Calmer, More Manageable Low-Back Pain
For pain that stays centered in the low back and is suspected to involve the facet joints, radiofrequency ablation may interrupt pain signals from selected medial branch nerves that serve those joints. Relief varies and is not permanent because the treated nerves can regenerate over time. A diagnostic medial branch block is generally used first to assess whether facet-mediated pain is likely before radiofrequency ablation is considered.
Better Standing and Walking Tolerance
Greater Stability When Instability Is Contributing to Pain
A Treatment Path Based on the Diagnosis and Patient’s Goals
The Interventional Back Pain Treatments Offered at the Portland Office

Epidural Steroid Injections for Radiating, Nerve-Related Back Pain
An epidural steroid injection places anti-inflammatory medication into the epidural space near irritated spinal nerve roots using an interlaminar, transforaminal, or caudal approach under image guidance. It is most relevant when back pain radiates into the buttock or leg from an irritated or inflamed nerve root, a pattern commonly described as sciatica. Conditions such as disc herniation or foraminal narrowing may contribute to this type of nerve-related pain. An epidural injection may reduce inflammation and provide temporary relief of radiating symptoms in selected patients, but it does not repair a damaged disc or open a narrowed spinal canal. Repeat injections are based on the patient’s response and documented benefit rather than a fixed schedule.
Radiofrequency Ablation for Facet-Joint Low-Back Pain
Radiofrequency ablation uses controlled thermal energy delivered through a needle electrode to interrupt pain signals traveling along selected medial branch nerves that serve the facet joints. It may be considered for chronic, predominantly axial low-back pain suspected to arise from those joints rather than for sciatica or spinal stenosis. A diagnostic medial branch block is generally performed first to help determine whether facet-mediated pain is likely. When effective, relief may last several months or longer, but it is temporary because the treated nerve can regenerate. The procedure reduces pain signaling rather than repairing the underlying arthritis.
Minimally Invasive Spinal Decompression for Structural Narrowing
When back and leg symptoms are associated with narrowing around the spinal nerves, decompression addresses the physical crowding itself. Dr. Fiks performs minimally invasive decompression procedures that may include the mild® Procedure for selected patients with lumbar spinal stenosis and ELID endoscopic decompression and discectomy when clinically appropriate. The specific approach depends on the location and cause of the narrowing, the patient’s symptoms, imaging findings, previous treatment, and overall health. These procedures are intended for appropriately selected patients rather than as a universal treatment for back pain.
Stabilization Procedures for Sacroiliac or Lumbar Instability
Spinal Cord Stimulation for Persistent Back Pain
For selected patients with persistent back or related nerve pain that has not responded adequately to other treatments, spinal cord stimulation may be considered as part of the treatment plan. Rather than decompressing the spine or stabilizing an unstable segment, spinal cord stimulation is used to modify the transmission of pain signals. It may therefore have a role when persistent pain remains despite previous treatment or when other approaches are not appropriate for the individual patient. Candidate selection depends on the diagnosis, type and location of pain, previous treatment response, overall health, and treatment goals.
Spinal Infusion for Palliation of Persistent Back Pain
Spinal infusion may be considered for the palliation and management of persistent back pain that has not responded adequately to more definitive treatment options. Unlike decompression or stabilization procedures, spinal infusion is intended primarily to help manage difficult chronic pain rather than correct a structural problem in the spine. Whether it is appropriate depends on the individual diagnosis, treatment history, response to previous care, medical considerations, and overall goals.
Multifidus Stimulation for Dysfunctional or Atrophied Postural Muscles
Spinal infusion may be considered for the palliation and management of persistent back pain that has not responded adequately to more definitive treatment options. Unlike decompression or stabilization procedures, spinal infusion is intended primarily to help manage difficult chronic pain rather than correct a structural problem in the spine. Whether it is appropriate depends on the individual diagnosis, treatment history, response to previous care, medical considerations, and overall goals.
Cluneal Nerve Stimulation for Cluneal Neuralgia
Diagnostic Evaluation and Matching the Right Treatment
Before any procedure, the team reviews the patient’s symptoms, medical history, and previous treatment, performs a physical and neurologic examination, and reviews X-ray, MRI, or CT imaging when clinically useful. Diagnostic injections, such as a medial branch block, may also help assess whether a particular joint, nerve, or spinal level is contributing to the pain.
Treatment selection considers not only the suspected pain source but also what the treatment is intended to accomplish. Depending on the diagnosis, the goal may be to reduce inflammation, interrupt or modify pain signaling, relieve nerve compression, stabilize an unstable joint or spinal segment, support rehabilitation of dysfunctional muscles, or palliate persistent pain that has not responded adequately to more definitive treatment.
Additional options at the practice may include kyphoplasty for painful compression fractures, basivertebral nerve ablation for vertebrogenic pain, and Regenexx regenerative care for selected spine conditions.
New loss of bladder or bowel control, saddle numbness, rapidly worsening leg weakness, back pain with fever, or pain after a major injury are warning signs that call for urgent medical evaluation rather than a routine appointment.
Each procedure has different risks, benefits, limitations, and alternatives. Possible complications vary according to the treatment and may include temporary soreness, bleeding, infection, medication or sedation reactions, nerve injury, or lack of benefit. Dr. Fiks reviews procedure-specific considerations and postoperative instructions before care.

Back Pain Services and Procedures Available at the Portland Office
- Comprehensive spine and back pain evaluation with physical, neurologic, and imaging review
- Epidural steroid injections using interlaminar, transforaminal, and caudal approaches
- Diagnostic medial branch blocks and facet joint injections
- Radiofrequency ablation for facet-mediated low-back pain
- Minimally invasive spinal decompression, including the mild® Procedure for lumbar spinal stenosis
- ELID endoscopic decompression and discectomy for selected patients
- Interspinous stabilization and fusion using StabiLink and InSpan for selected patients
- Sacroiliac joint fusion for selected patients with appropriately diagnosed SI joint pain or instability
- Minimally invasive lumbar fusion or stabilization for selected patients with lumbar instability
- Basivertebral nerve ablation for vertebrogenic low-back pain, known as the Intracept™ Procedure
- Kyphoplasty for painful spinal compression fractures
- Spinal cord stimulation for appropriate chronic back and nerve-related pain conditions
- Spinal infusion for selected patients requiring palliation of persistent pain
- Multifidus stimulation for selected patients with dysfunctional or atrophied postural muscles
- Cluneal nerve stimulation or peripheral nerve stimulation for selected patients with cluneal neuralgia
- Fluoroscopic and, when appropriate, ultrasound guidance for spinal procedures
- Regenexx regenerative options for selected spine conditions
- Coordination with trusted outside partners for physical therapy and behavioral support
The Portland Providers Who Diagnose and Treat Back Pain at the Practice
Every back pain plan at the practice is guided by the licensed providers below, whom patients often describe as professional, kind, and genuinely invested in finding solutions.
Vladimir Fiks, MD | Interventional Pain Management Physician and Regenexx Provider
Vladimir Fiks, MD, is the interventional pain physician who leads back pain care at Advanced Pain Management Center and performs the practice’s minimally invasive spinal decompression procedures. He graduated from Saratov University, completed an internship at Jefferson Frankford Hospital in Philadelphia, and then finished both an anesthesiology residency and a pain management fellowship at Oregon Health & Science University in Portland. As a Regenexx physician, he focuses on image-guided, interventional orthopedic care and practices both medical and interventional pain therapies through an integrative approach. Dr. Fiks speaks Spanish, English, and Russian, and he continues to expand his medical education so that patients benefit from his thoroughness.
“I have had remarkable results from my treatments at this center. My treatments have been for low back pain that goes into my legs and feet. If you are looking for a way to help your pain without surgery this is the place. They are very professional and kind. I wish it was easier to do more follow ups with Dr Fix himself instead of his staff. But he is a very busy doctor! But do yourself a favor and check out all they can do for back and neck pain before going for surgery. Best choice I have ever made to help with my chronic pain.”
Dmitriy Shore, PA-C | Interventional Pain Medicine Provider
Dmitriy Shore, PA-C, has devoted his career to the treatment of chronic pain conditions and helps identify appropriate candidates for back pain procedures while supporting patients through recovery alongside Dr. Fiks and the nursing team. He has been board-certified by the National Commission on Certification of Physician Assistants since graduating from Oregon Health & Science University in 2000. A naturally curious clinician, he actively pursues continuing education and reviews the pain management literature to keep his care current. Patients describe him as an advocate who treats their well-being as a priority.
“Dr. Shore continues to try and help me find solutions to my chronic back pain. I always feel that my well being is of upmost importance. Chronic pain affects every area of your life and It’s nice to feel like you have an advocate on your side.”
Alberto Rodriguez, PA-C, MS | Interventional Pain Medicine Provider
Alberto Rodriguez, PA-C, MS, earned a Master of Science degree and completed his Physician Assistant studies at Pacific University in 2008, after undergraduate work at Central Washington University. Since completing his physician assistant studies in 2008, he has provided patient-centered care across orthopedics, urgent care, family medicine, and pain management, a background that helps him evaluate complex conditions and build individualized plans. He helps identify appropriate candidates for interventional back pain care and supports patients through recovery. He believes exceptional care begins with listening, and he takes time to educate each patient and partner with them in decisions about their treatment.
Quick Answers for Portland Patients Considering Back Pain Care
Is Advanced Pain Management Center actually located in Portland?
Yes. The office is at 10305 SW Park Way, Suite 300, in the West Haven area of southwest Portland near Providence St. Vincent Medical Center. Interventional back pain care and procedures are provided at that Portland location.
Can the practice help with back pain that started after a car accident?
Yes. Advanced Pain Management Center evaluates back pain associated with auto accidents. The assessment considers the injury history, symptoms, examination findings, previous care, and imaging when clinically appropriate before treatment is recommended.
Will I be put under general anesthesia for these back pain procedures?
Anesthesia and sedation depend on the procedure. Spinal injections are generally performed using local anesthesia, while APMC’s minimally invasive decompression procedures are performed with local anesthesia and IV sedation on an outpatient basis. Decompression patients are typically discharged after approximately one hour of recovery when clinically appropriate. The care team will explain the protocol for the specific procedure.
Portland Neighborhoods and Nearby Communities the Practice Serves
Patients reach the SW Park Way office from across Portland and the surrounding area. Common places patients travel from for back pain care include:
- Portland, OR 97225, including the West Haven and Cedar Mill areas
- Downtown Portland and the financial district
- Pearl District and Northwest Portland
- South Waterfront
- Goose Hollow and Hillsdale
- Multnomah Village and Raleigh Hills
- Rose Quarter, Lloyd District, and the Central Eastside
- Sylvan and the US-26 corridor
- Southwest Portland near Providence St. Vincent Medical Center
- The greater Portland area and Southwest Washington
- Beaverton
- Tigard
- Hillsboro
- Lake Oswego
How Back Pain Care Fits Into a Portland Week
Portland runs on movement, from morning walks across the river bridges and along the waterfront to long weekday hours at downtown desks and weekend recreation whenever the rain lets up. Chronic back pain quietly chips away at all of it, turning a simple errand or a night at the Moda Center into something to think twice about. The practice is located in Portland’s West Haven area and offers weekday appointments for evaluations, procedures, and follow-up care. Patients can contact the office to discuss scheduling and visit logistics before symptoms become more limiting.
Set Up a Back Pain Evaluation in Portland
Call (503) 295-0730 or schedule a back pain evaluation online with the Advanced Pain Management Center team. The front desk can explain what to bring, discuss appointment logistics, and note whether the pain began after an injury or accident so that the relevant history is available for the visit.
- Address: 10305 SW Park Way, Suite 300, Portland, OR 97225
- Website: https://apmconline.org/
- Hours: Monday to Friday: 8:00 AM to 5:00 PM. Saturday: Closed. Sunday: Closed
Advanced Pain Management Center 10305 SW Park Way, Suite 300, Portland, OR 97225
Frequently Asked Questions About Interventional Pain Management for Back Pain Portland
How can I tell if my back pain is serious?
Most back pain is not dangerous, but certain signs warrant prompt evaluation, including pain that follows a significant injury, comes with fever, or brings new numbness, weakness, or loss of bladder or bowel control. Pain that steadily worsens, disturbs sleep, or does not improve over several weeks is also worth having checked.
Is it normal to have back pain every day?
Occasional aches are common, but daily back pain that lingers for weeks is a reason to be evaluated rather than something to simply live with. Persistent pain may have one or more contributing causes, and a clinical evaluation is the first step toward determining which plan may be appropriate.
What are common causes of back pain?
Back pain may involve the muscles, ligaments, discs, facet joints, nerves, spinal canal, or other structures. Conditions such as disc herniation, arthritis, spinal stenosis, instability, or a compression fracture may also contribute. Because back pain is a symptom rather than one diagnosis, the evaluation considers which factors may be contributing in each patient.
What should I avoid when I have back pain?
Unless a clinician has advised otherwise, prolonged bed rest is generally discouraged. Avoid activities that clearly worsen the pain, including heavy lifting or sudden twisting during an acute flare. The appropriate level of movement depends on the cause, severity, injury history, and any neurological symptoms.
Can stress cause back pain?
Stress can contribute to back pain by increasing muscle tension and by making existing pain feel more intense. It is rarely the whole story, so stress-related tension is best considered alongside a proper evaluation of the spine rather than in place of one.
For back pain, is an MRI or a CT scan better?
It depends on what a provider suspects. MRI is generally better for soft tissues such as discs, nerves, and the spinal cord, while CT shows bone detail well, and X-rays are often used first for alignment and degenerative changes. The right study is chosen based on your symptoms and examination.
What tests are done for back pain?
Evaluation usually begins with a history and a physical and neurologic examination, followed by imaging such as X-ray, MRI, or CT when it is clinically useful. Diagnostic injections, such as a medial branch block, may also be used to help assess whether a specific joint, nerve, or spinal level is contributing to the pain.
When should I not ignore back pain?
Do not ignore back pain that comes with new bladder or bowel changes, saddle numbness, rapidly worsening leg weakness, fever, or that follows major trauma, since these can signal a problem needing urgent care. Pain with a history of cancer or unexplained weight loss also deserves prompt attention.
What vitamins help with back pain?
No vitamin routinely treats back pain. A confirmed vitamin deficiency may affect bone, muscle, or nerve health, but supplementation should be based on an individual’s medical history, diet, medications, and, when appropriate, laboratory testing. Ask a clinician before starting a supplement specifically for back pain.
At what age is back pain most common?
Back pain can occur at any age. Some degenerative conditions become more common later in life, while injuries, muscle strain, disc problems, inflammatory conditions, and other causes may affect younger adults as well. Age alone does not determine the cause or appropriate treatment.
What is interventional pain management for back pain?
Interventional pain management for back pain uses minimally invasive and image-guided treatments selected according to the diagnosis, symptoms, and treatment goals. Options may include spinal injections, radiofrequency ablation, decompression and stabilization procedures, spinal cord or peripheral nerve stimulation, and other targeted treatments. The goal is to reduce symptoms, improve function, or manage persistent pain using an approach appropriate to the individual condition.
Can chronic back pain be treated without surgery?
Many patients begin with nonsurgical care such as medication, referred physical therapy, activity modification, or injections. Radiofrequency ablation is also minimally invasive. Spinal decompression and fusion procedures are still medical or surgical procedures, even when performed through smaller access points than traditional open surgery. The appropriate path depends on the diagnosis, symptoms, anatomy, previous care, and overall health.
How long does an epidural steroid injection last for back pain?
Relief varies widely and is generally temporary, sometimes lasting from several weeks to a few months. Some patients respond better than others. When appropriate, injections may be combined with activity modification, exercise, or referred physical therapy. Repeat injections are guided by the patient’s response and documented benefit rather than a fixed schedule.
How long does radiofrequency ablation relief last for back pain?
When it helps, relief may last several months and sometimes longer, but it is temporary because the treated nerve can regenerate. If pain returns, repeat treatment may be considered after another evaluation and review of the previous response, current symptoms, and coverage requirements.
What kind of doctor should I see for chronic back pain?
An interventional pain management physician evaluates possible sources of spine pain and provides image-guided and minimally invasive treatments when appropriate. The physician may also coordinate with physical therapy, surgical specialists, or other providers. At Advanced Pain Management Center, Dr. Fiks provides interventional procedures and minimally invasive spine care according to the patient’s diagnosis and treatment needs.
Back Pain Health Resources From Advanced Pain Management Center
To learn more about back pain and the ways it can be evaluated and treated, explore the related procedures and articles below from Advanced Pain Management Center in Portland, OR.
Back pain services and procedures
- Spine Pain Treatment in Portland, OR
- Spinal Injections
- Radiofrequency Ablation
- Spinal Decompression
- Injection Therapies
- Vertebrogenic Pain and Basivertebral Nerve Ablation (Intracept™)
- SI Joint Fusion
- Minimally Invasive Spinal Fusion
- Spinal Cord Stimulation
- Spinal Infusion
- Peripheral Nerve Stimulation
- Kyphoplasty
- Regenexx for Spine Conditions
Articles from the APMC pain management blog
Meet the physician
Back Pain Care in Portland That Starts With a Focused Evaluation
If you are tired of planning life around back pain, Advanced Pain Management Center will take the time to evaluate what may be contributing to the symptoms, explain which options may fit in plain language, and focus on both day-to-day comfort and function. Contact the Portland team when you are ready to schedule an evaluation.
Take the First Step Toward Back Pain Relief in Portland
Schedule Your Portland Back Pain Evaluation | Call (503) 295-0730
Advanced Pain Management Center 10305 SW Park Way, Suite 300, Portland, OR 97225
Hours:
- Monday to Friday: 8:00 AM to 5:00 PM
- Saturday: Closed
- Sunday: Closed



